Call us on T: 01709 464 200. We are open Mon-Fri 9am-5pm.

Call us on T: 01709 464 200. We are open Mon-Fri 9am-5pm.
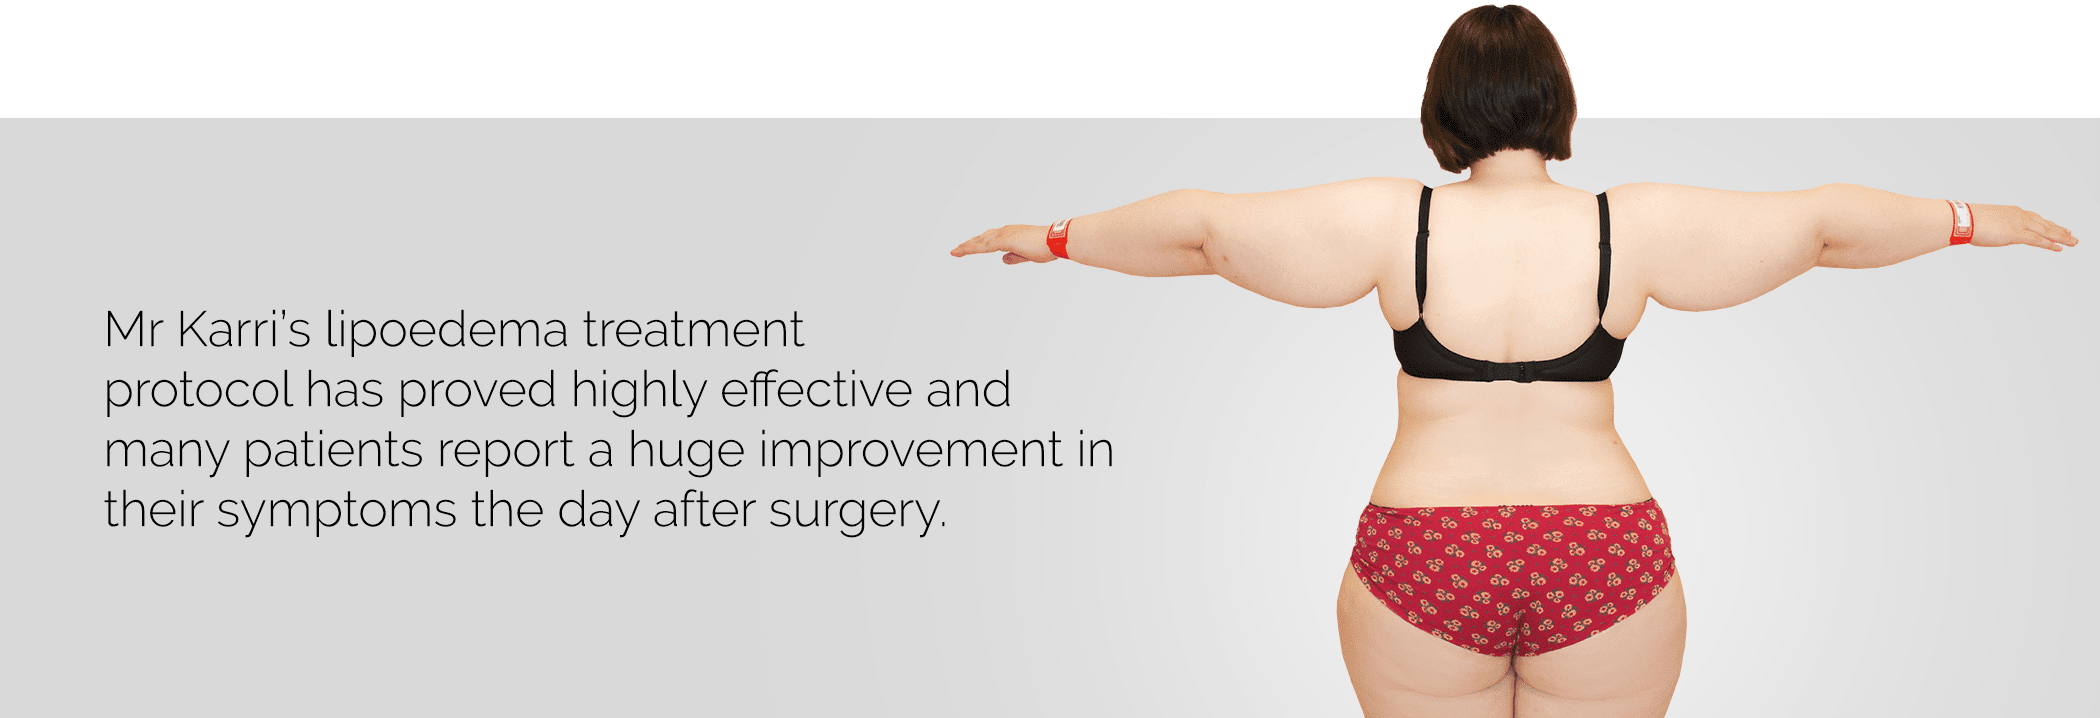 Lipoedema is a condition characterised by abnormal, symmetrical fat deposition in the extremities, typically the lower limbs. The circumferential enlargement of the lower limbs typically extends from the hips to the ankles but never involves the feet. As a result, the lower body becomes disproportionately larger than the upper body.
Lipoedema almost exclusively affects females and approximately 10% of the female population. In 70% of cases the abnormal fat distribution affects the lower limbs and in 30% of cases the upper limbs are also affected. The cause of lipoedema is unknown but a genetic and hormonal involvment is suspected. Its onset or exacerbation often coincides with periods of hormonal disturbance such as puberty, pregnancy and peri-menopause.
In males lipoedema is extremely rare and occurs as a result of hormonal disorder.
Other clinical features include;
Many women feel a sense of frustration as the excess fat is generally resistant to diet and exercise. The growing sense of frustration as the disease progresses often leads women to overeat and gain weight. About 50% of patients end up suffering from obesity in addition to the lipoedema.
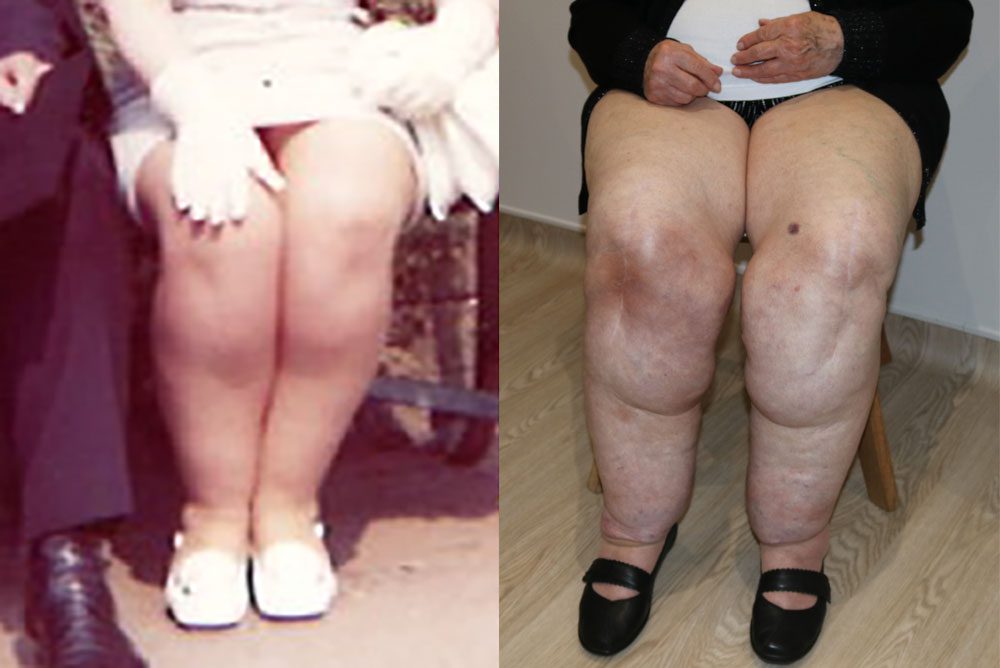
Lipoedema is a progressive condition, which means it only worsens with time. These photos show the same lipoedema patient 45 years apart. The lower limbs have progressively enlarged, particularly the pretibial fat pads. During this time the patient has suffered pain in both lower limbs and typical of many lipoedema patients, undergone bilateral knee replacements.
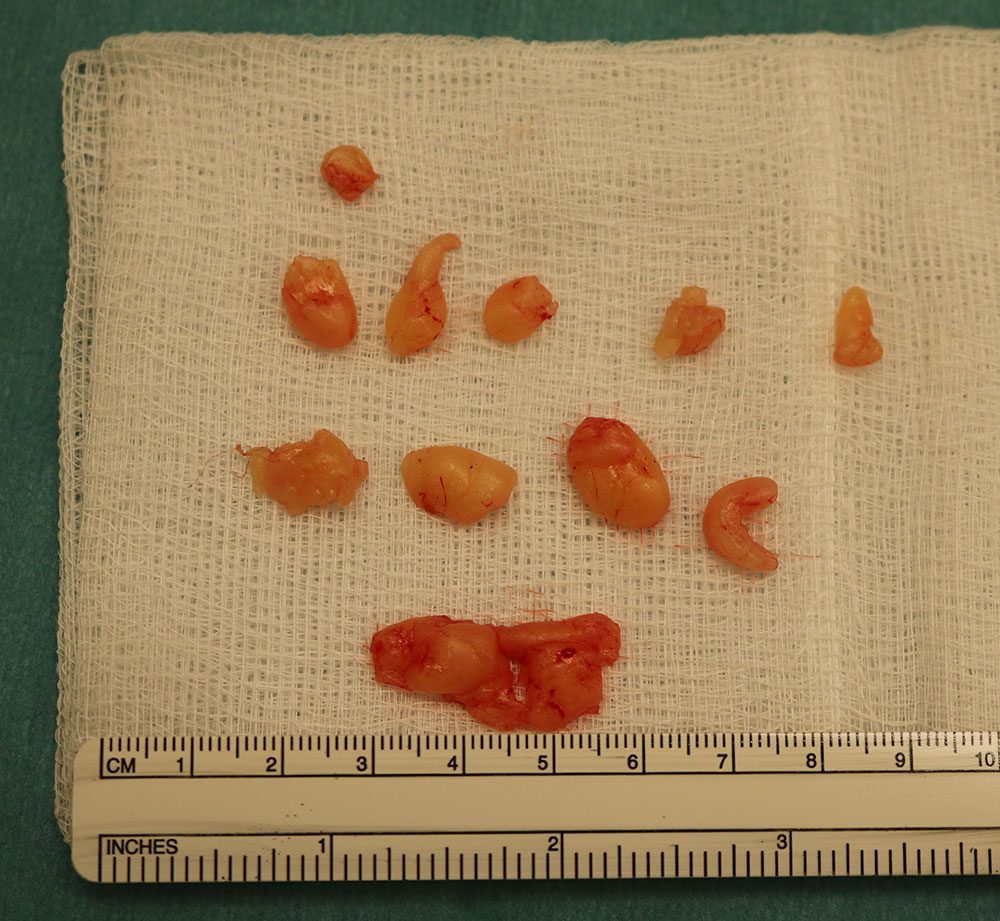
One of the unusual features of the lipoedema is the nodular consistency of the subcutaneous fat. This is particularly evident in Stage II disease, in which patients can feel hard lumps within the fat.
The characteristic symptoms of lipoedema include;
Slow, progressive increase in lower limb circumference, usually at puberty, pregnancy or menopause
Non-specific pain in the lower limbs
Pressure-induced pain (some patients report intolerable pain when having injections into their lower limbs or if they have weight placed on their legs. Even the lightest pressure can cause pain)
Tendency to bruise easily
Lower back pain
Knee pain (or a history of knee osteoarthritis)
Patella dislocation
Absence of hair growth on legs
Pitting oedema at the ankles at the end of the day
Low mood or depression
The signs associated with lipoedema are diverse and include column-like appearance of the lower limbs, ‘pantaloon’ ankle deformity, sparing of the feet, nodular consistency of subcutaneous fat, tenderness on palpation (particulraly the thighs and lower back), limbs feeling cold on palpation, varicose veins, negative Stemmer’s sign, reduced skin elasticity and cellulite-like appearance of the skin.
There are few objective criteria for diagnosing lipoedema. The combination of typical symptoms and signs support the diagnosis. The clinical experience of the clinician is often the major determinant in obtaining the correct diagnosis.
For the diagnosis of lipoedema, Mr Karri has devised a scoring system which has proved to have a very high sensitivity and specificity.
One of the hallmark features of lipoedema is a tendency to bruise easily, which reflects capillary fragility. Patients often report bruises arising spontaneously or after minor injury.
Read NICE guidance on lipoedema liposuction

Importance of specialist assessment
Every lipoedema patient is unique and has their own challenges. Patients present in a variety of ways, with some having intense soft-tissue pain whereas others have predominantly excess fat and profound body disproportion. Treatment must be thoroughly planned, taking into account the areas to be treated, timing between sessions of liposuction and co-existing medical issues. It is therefore essential lipoedema patients are treated by a specialist with extensive experience with lipoedema, such as Mr Karri.
The European Lymphology Society (ELS) has identified 5 types of lipoedema, based the distribution of abnormal fat.
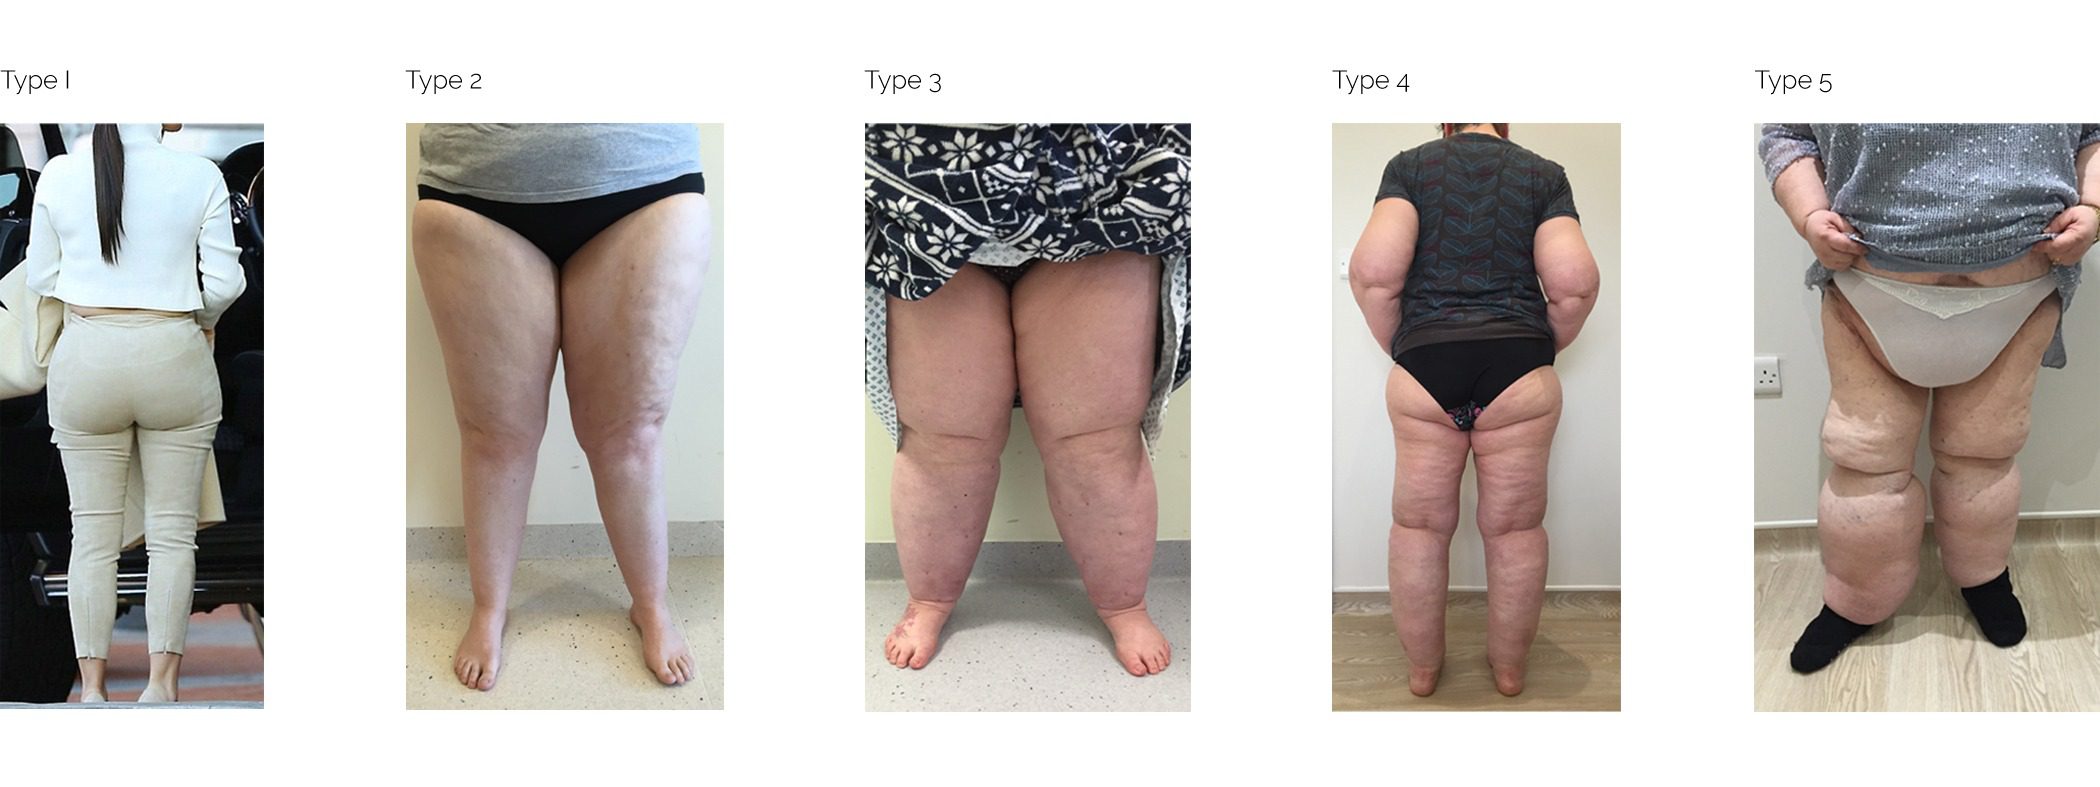
Type 1. Buttock & hips (saddle bag phenomenon)
There are some patients who appear to present with types I or II lipoedema but actually have ‘female-pattern gluteofemoral obesity’. This is a distinct entity from lipoedema, for which there is a recognised natural history and patients report fat-loss during lactation.
Another condition often confused with types I and II lipoedema is steatopygia. This is the excessive accumulation of fat on the buttocks and thighs, particularly prevalent in women of African origin.
Type II. Buttocks to knees
Type III. Buttocks to ankles
Type IV. Arms & legs affected
Type V. Lipo-lymphoedema
Three stages of lipoedema have been described, based on changes in the texture of the limb and development of skin folds.
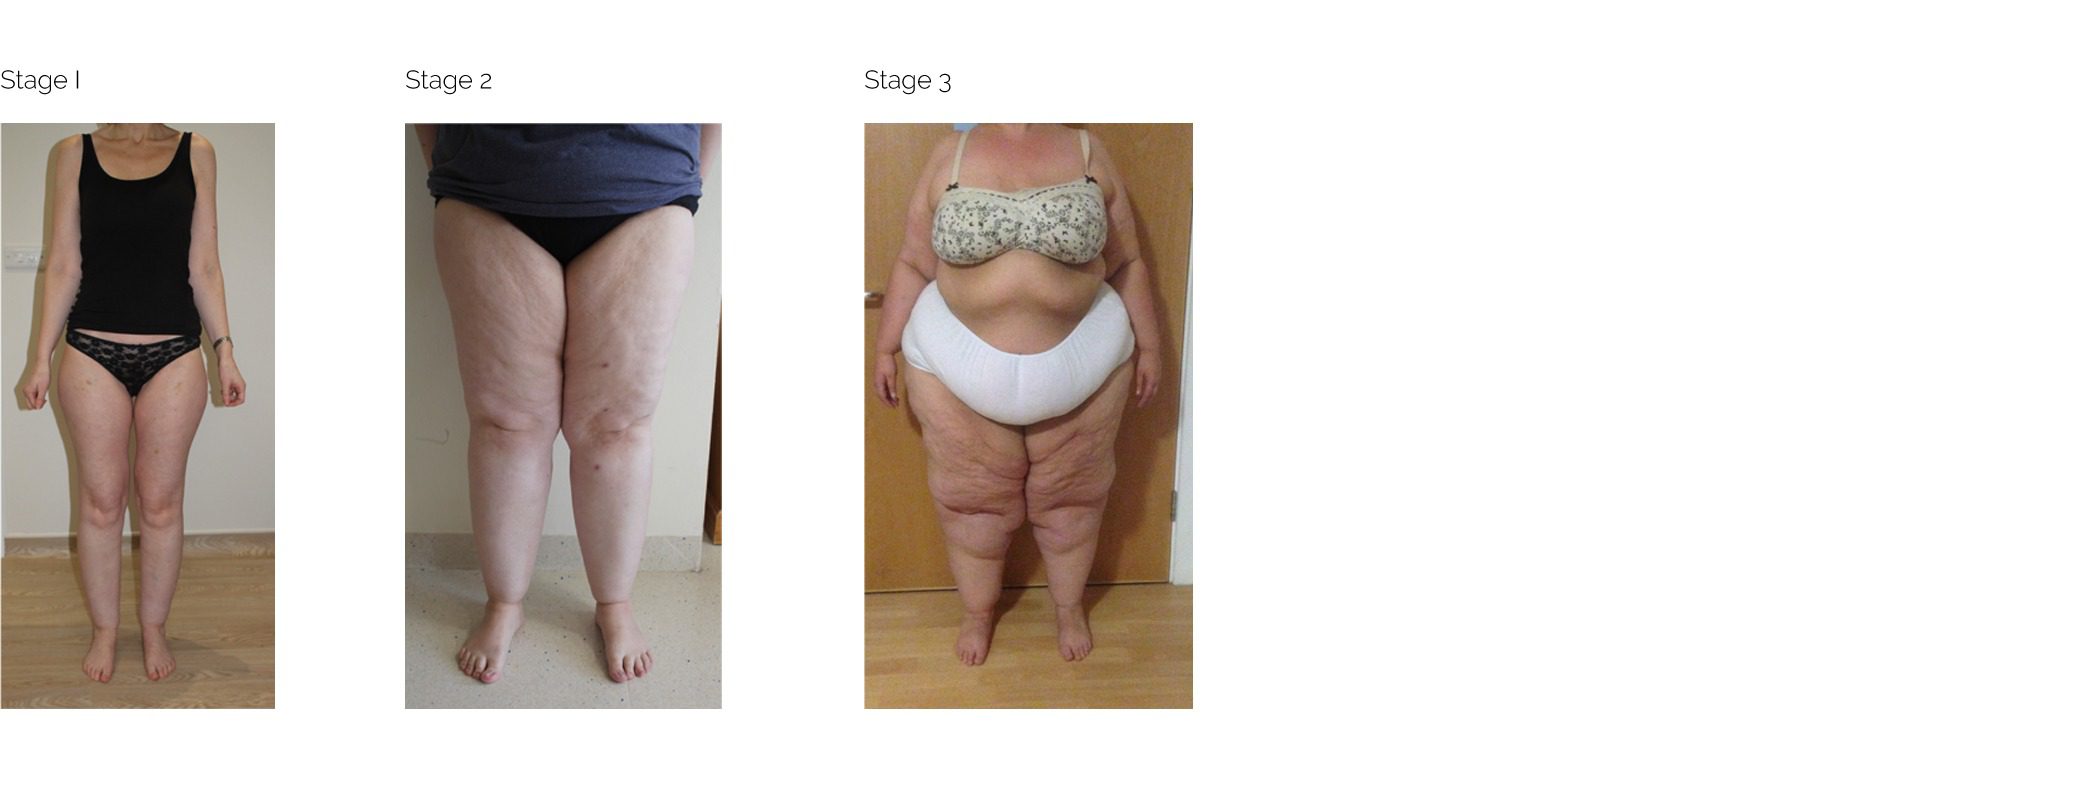
Stage I: has a normal skin surface. The subcutanous fatty tissue has a soft consistency but multiple small nodules can be palpated ("orange-peel skin"). This stage can last for several years.
Stage II: the skin surface becomes uneven and harder due to the increasing nodular structure (big nodules) of the subcutaneous fatty tissue ("mattress skin")
Stage III: lobular deformation due to increased fatty tissue; palpable nodules varying in size from a walnut up to a fist; large, deforming folds of fat. Skin bulges are most common around the medial knee.Why is lipoedema not well recognised in the medical community?
There are many reasons why health professionals do not recognise or understand lipoedema. Part of the problem is that lipoedema is not formally recognised as a disease in the international disease classification system. Fat disorders receive no attention or very little attention during undergraduate and postgraduate medical training, there is little understanding about the cause and natural history of lipoedema, and there is difficulty in making a diagnosis.
To address the lack of awareness amongst family doctors in the United Kingdom, the Royal College of General Practitioners has published an e-learning course on lipoedema. What is the prognosis of lipoedema?
Lipoedema is a progressive condition, however the rate of progression varies between patients. Furthermore, the presence of co-morbidities such as generalised obesity, lymphoedema, peripheral vascular disease and diabetes can significantly worsen symptoms and quality of life. Lipoedema women who pursue an active lifestyle, eat a balanced diet and maintain their weight generally have a better prognosis than those who do not.
Lipoedema Treatment
Treatments for lipoedema can be broadly divided into non-surgical therapies and liposuction.
Non-surgical therapies do not reduce the volume of limbs but can provide relief of symptoms, such as pain and oedema. Furthermore, there is no evidence to indicate non-surgical therapies slow progression of the disease. Non-surgical therapies include;
Compression hosiery - may be in the form of below-knee socks, stockings or garments. They work by providing the muscles with a firm resistance to work against, thereby improving the function of the lymphatic system. Fluid within the limb is moved towards the body, where it is drained more easily. Compression on the limb also prevents excess fluid transfer from the circulation into the soft tissue. Compression hosiery is therefore ideally suited for lipoedema women with lipo-lymphoedema or orthostatic oedema.
Manual lymphatic drainage (MLD) - a type of gentle massage that stimulates lymphatic flow, thereby alleviating oedema and associated pain and discomfort. MLD should ideally be performed in combination with compression hosiery or bandaging. Further details regarding MLD can be found at www.mlduk.org.uk.
Intermittent pneumatic compression - a mechanical device that provides massage to a limb using inflatable chambers. The segmental massage encourages lymphatic flow in the limb thereby alleviating oedema and associated pain and discomfort. This therapy may not be tolerated by lipoedema patients who have pressure-induced pain.
Exercise - suitable types of exercise are swimming, cycling and power-walking, which all serve to improve lymph flow).
Weight loss / diet (an anti-inflammatory diet) - has been advocated by many lipoedema patients who report a reduction in oedema and pain.Liposuction
In contrast to non-surgical therapies, liposuction is the only treatment that can achieve a volume reduction in the limb. Liposuction also reduces the weight of the limb, pressure-induced pain and can improve knee range-of-motion.
From Mr Karri’s extensive experience with lipoedema liposuction, better outcomes are achieved in early-stage lipoedema than late-stage lipoedema. In late stage lipoedema soft-tissue fibrosis, knee osteoarthritis and concurrent generalised obesity can all lessen the positive impact of liposuction.
Liposuction should not be considered a quick-fix and every patient requires a comprehensive evaluation, examination and treatment plan. Patients may be declined for liposuction if they have been misdiagnosed with lipoedema or if their expectations are unrealistic.
Lipoedema is a fat disorder characterised by abnormal, symmetrical fat deposition in the limbs – most often the legs, that exclusively affects women. The enlargement runs from the hips to the ankles but never involves the feet, which is one of the features that distinguishes it from lymphoedema. The lower limbs (and upper limbs in some cases) become disproportionately large compared to the torso.
The abnormal fat is diet and exercise resistant and cannot be reduced by weight loss or exercise, which distinguishes it from obesity.
Lipoedema is more common than people think, and it has been estimated to affect around 10% of the female population. In 70% of cases it affects the legs alone; in 30% the arms are affected too. The cause is unknown, though a genetic and hormonal involvement is suspected – onset or worsening often coincides with times of hormonal change i.e. puberty, pregnancy or the peri-menopause.
Yes – they are the same condition. Lipoedema is the British spelling and lipedema the American one. UK patients search both, and you will see both used by support groups and clinicians. This website uses the British spelling throughout.
No. Lipoedema is a chronic, progressive condition. It worsens with time, though the rate varies considerably between patients. It is believed that lipoedema only worsens with increasing weight gain. Existing conditions such as generalised obesity, lymphoedema, peripheral vascular disease and diabetes can significantly worsen symptoms and quality of life.
Women with lipoedema who stay active, eat a balanced diet and maintain their weight generally have a better outlook than those who do not.
Liposuction is the only treatment that reduces the volume of the limb. It also reduces the weight of the limb and soft-tissue pain, and can improve mobility and knee range of motion.
Non-surgical therapies such as compression garments, dry brushing, vibration plate, manual lymphatic drainage (MLD), intermittent pneumatic compression, exercise and diet, can relieve symptoms such as pain and swelling, but they do not reduce limb volume, and there is no evidence that they slow progression of the disease. Please bear in mind, that for the vast majority of sufferers, non-surgical therapies are ineffective.
Outcomes are better when surgery is performed for early-stage than late-stage lipoedema. In late-stage disease, soft-tissue fibrosis, knee osteoarthritis and co-existing obesity can all reduce the benefit of surgery.
A consultation for lipoedema surgery with Mr Karri costs £250 (correct as of Sept 2026) and typically lasts 45 minutes. Every patient is welcome to a second consultation before their procedure, free of charge, in person or virtually. There are no fees for follow-up appointments.
The cost for lipoedema surgery is bespoke because treatment is planned around the areas to be treated and the number of operations needed. You will be given a personalised quote after your consultation with Mr Karri. See our fees for published prices.
It depends on what Type and Stage of lipoedema you have. Generally speaking, those with Stage 1 disease only need one operation, while those with Stage 2 or 3 disease will need multiple operations, with the potential for more if there is skin laxity and body contouring is needed. Mr Karri will set out a treatment plan for your presentation at your consultation.
Yes. Liposuction for lipoedema is not a quick fix, and every patient has a full evaluation, examination and treatment plan before surgery is agreed. Patients may be declined if they have been misdiagnosed with lipoedema, if their expectations of what surgery can achieve are unrealistic, if they have serious comorbidities that preclude surgery, or if they would benefit from weight loss treatment with GLP-1 drugs or surgery before the lipoedema liposuction.
There are few objective criteria for diagnosing lipoedema – diagnosis rests on the combination of typical symptoms and signs, and the experience of the doctor is often the deciding factor in getting it right. Lipoedema is also poorly recognised in general medical training, which is why many women go years without a diagnosis.
For that reason it matters that lipoedema is assessed and treated by someone with extensive experience of the condition. Mr Vasu Karri is a Consultant Plastic Surgeon on the GMC specialist register for plastic surgery, certified by the Royal College of Surgeons of England. He is the only Plastic Surgeon in the UK who has published his outcome data in a peer-reviewed medical journal (Improvement in Health-Related Quality of Life and Symptoms Following Lipedema Liposuction: A Longitudinal Study, Annals of Plastic Surgery 2025 – you can read it here).